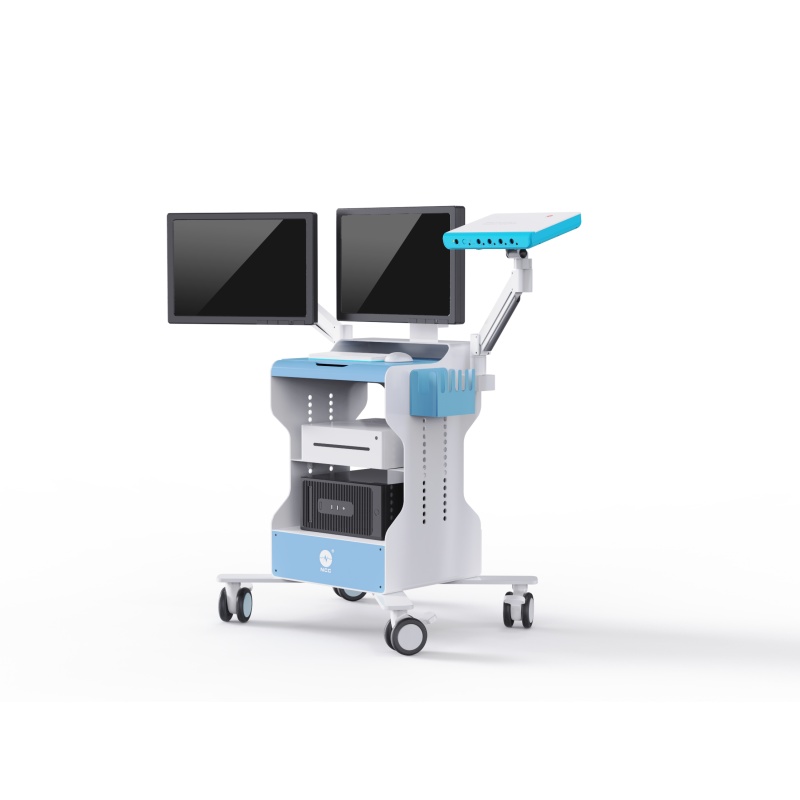
This case report describes multimodal intraoperative neurophysiological monitoring during UBE decompression for thoracic ossification of the ligamentum flavum, focusing on SEP, MEP, EMG changes, and anesthetic considerations.
Patient information: A 52-year-old woman with thoracic ossification of the ligamentum flavum and thoracic spinal canal stenosis underwent UBE surgery for decompression. Before surgery, movement of both lower limbs was normal.
Surgical objectives: to relieve neural compression, preserve lower-limb function to the greatest extent possible, achieve minimally invasive decompression, alleviate pain and weakness, and improve the patient's quality of life.
Common neurophysiological monitoring techniques used during UBE surgery for thoracic ossification of the ligamentum flavum include somatosensory evoked potentials (SEP), motor evoked potentials (MEP), and free-run electromyography (EMG). SEP assesses the integrity of the dorsal columns and sensory pathways; MEP assesses the integrity of the ventral spinal cord, corticospinal tracts, and motor pathways; and EMG is mainly used to detect direct nerve-root stimulation in real time, allowing immediate intraoperative alarms and avoidance of mechanical nerve injury. The parameter settings and monitoring findings for each modality are described below.
1) Electrode montage
Recording electrode: cortical Cz; reference electrode: Fz.
Stimulation electrodes: the bilateral posterior tibial nerves at the ankles.
2) Recording and stimulation parameters
Recording parameters: low-frequency filter, 30 Hz
high-frequency filter, 500 Hz
sweep speed, 10 ms
sensitivity, 2 μV
Stimulation parameters: stimulation frequency, 2.33 Hz
pulse width, 200 μs
stimulation intensity, 30 mA (constant current)
3) Monitoring points: Before surgery, confirm whether the patient has numbness in the lower limbs and whether a preoperative EMG examination is available; if so, it may serve as a reference for intraoperative monitoring. Continuous monitoring should be maintained throughout the procedure, with attention to changes in SEP waveforms. A decrease in amplitude of ≥50% or a latency prolongation of ≥10% suggests possible impairment of the ascending sensory pathway; the relevant maneuver should be stopped immediately and the need for decompression assessed. The motor pathway should also be monitored using complementary modalities to reduce the risk of postoperative lower-limb weakness, paralysis, or motor dysfunction.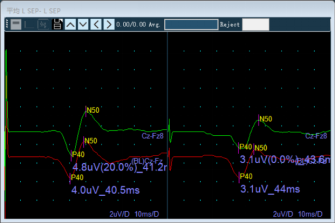
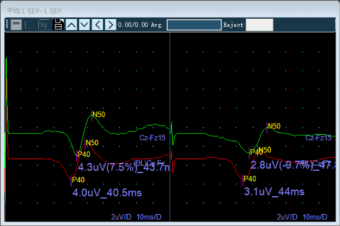
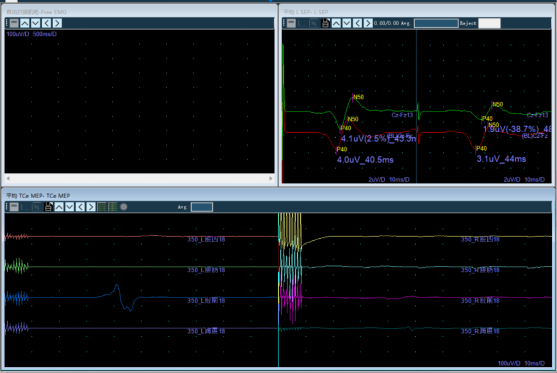
Preoperative baseline; Right-sided SEP decreased during laminar troughing and bony fenestration
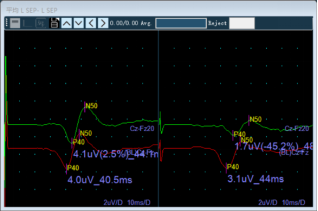
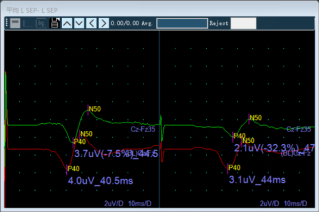
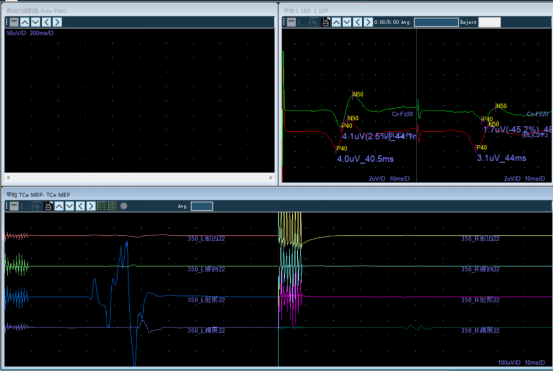
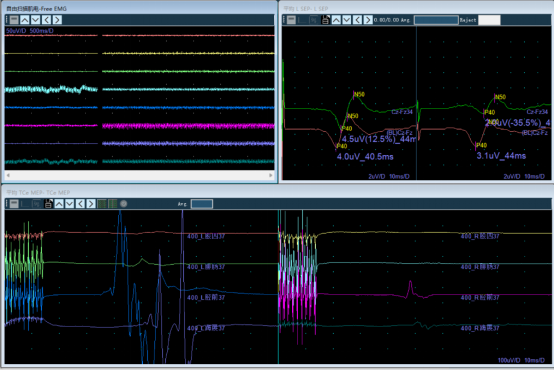
Right-sided SEP decreased during removal of the ossified ligamentum flavum and decompression; it increased during closure, showing a trend toward recovery
1) Electrode montage
Recording electrodes: bilateral quadriceps, tibialis anterior, gastrocnemius, and abductor hallucis muscles.
Stimulation electrodes: transcranial stimulation of the motor cortex, with electrodes placed at C1 and C2.
2) Recording and stimulation parameters
Recording parameters: low-frequency filter, 30 Hz
high-frequency filter, 3000 Hz
notch filter, off
sweep speed, 10 ms
sensitivity, 50 μV
Stimulation parameters: pulse polarity, biphasic
train count, 9 pulses
pulse width, 100 μs
train frequency, 1000 Hz
stimulation voltage, 300 V
3) Monitoring points: Before surgery, confirm whether the patient has lower-limb weakness and assess muscle strength. Because MEP stimulation may cause patient movement, the surgeon must be instructed to pause the procedure before stimulation. If the SEP amplitude decreases by ≥30% or latency is prolonged by ≥10%, MEP monitoring should be intensified and the MEP waveform interpreted together with SEP findings to assess possible neurological injury. MEP may also be monitored synchronously when intraoperative imaging is required. Disappearance or an abrupt decrease in MEP amplitude suggests possible acute injury to the motor pathway; the hazardous maneuver should be stopped immediately. The purpose of MEP is to provide real-time warning of injury to the motor conduction pathway and reduce the risk of postoperative lower-limb weakness, paralysis, and motor dysfunction.
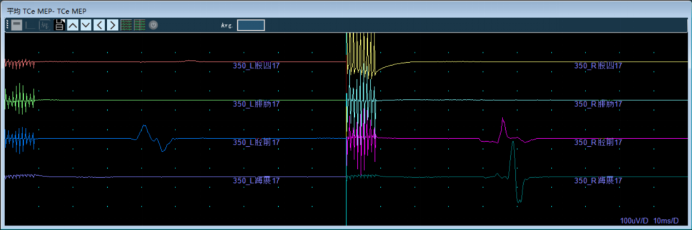
Preoperative baseline (residual neuromuscular blockade)
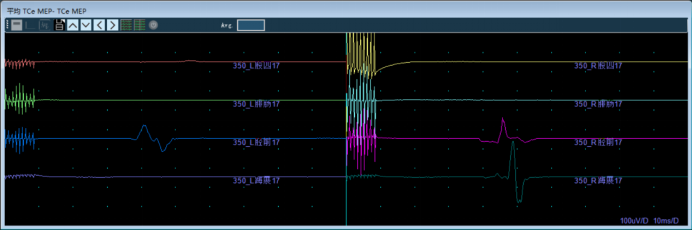
MEP monitoring during laminar troughing and bony fenestration
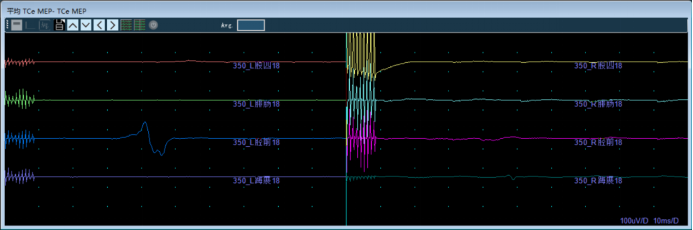
Right-sided MEP waveform decreased during removal of the ossified ligamentum flavum
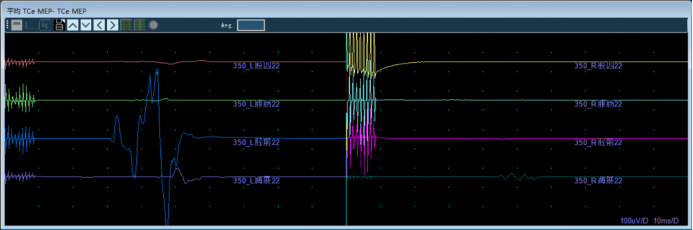
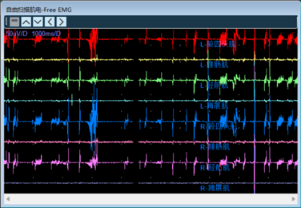
During decompression, prominent right-sided EMG bursts occurred, accompanied by a >50% decrease in right-sided MEP after neuromuscular blockade had fully resolved.
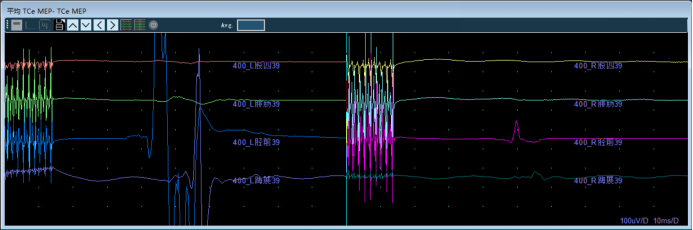
The right-sided MEP waveform showed a trend toward recovery during postoperative closure
1) Electrode montage
Recording electrodes: typically placed over the quadriceps, tibialis anterior, gastrocnemius, and abductor hallucis muscles.
2) Recording parameters
Recording parameters: low-frequency filter, 30 Hz
high-frequency filter, 3000 Hz
sweep speed, 100 ms
sensitivity, 50 μV
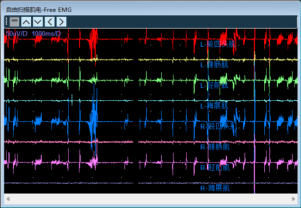
3) Monitoring objective: to detect direct stimulation of the nerve roots in real time, enabling immediate intraoperative alarms and avoidance of mechanical nerve injury. Bursting or sustained EMG activity suggests that a nerve root may be undergoing mechanical stimulation (contact, traction, or compression); the maneuver should be stopped immediately and the instrument position adjusted.
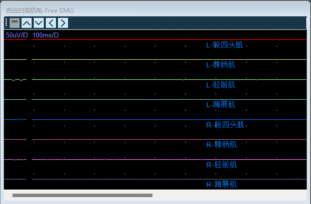
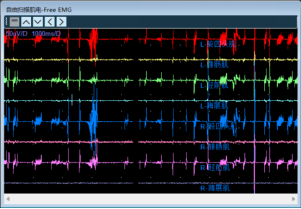
Preoperative EMG signal; EMG bursts during removal of the ossified ligamentum flavum
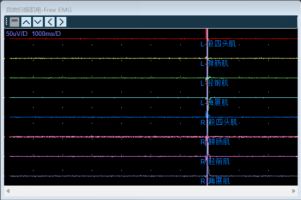
EMG bursts during decompression
At the beginning of surgery, during needle placement and endoscope insertion, the EMG signal showed resting activity and the SEP waveform remained stable. Because the neuromuscular blockade had not completely resolved at that time, the MEP amplitude was relatively low. A preoperative baseline was established for intraoperative comparison.
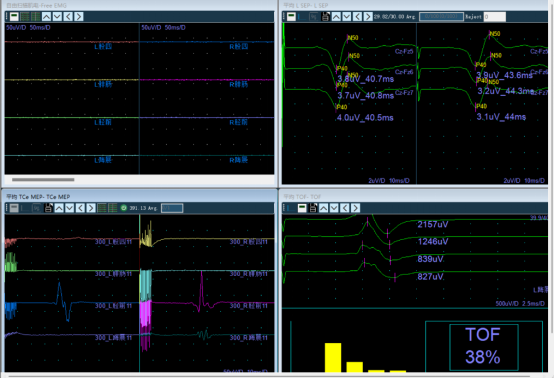
Monitoring changes during key surgical stages:
Laminar troughing and bony fenestration were the first high-risk steps. Changes in SEP and MEP were closely monitored. No marked MEP change was observed during this stage, although the neuromuscular blockade had not completely resolved; the right-sided SEP subsequently decreased by approximately 10%.
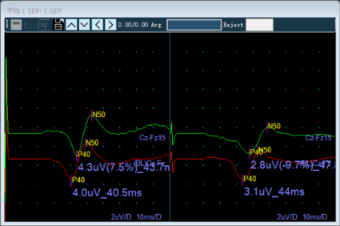
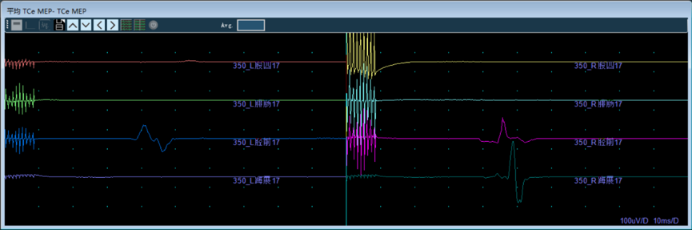
EMG, SEP, and MEP were monitored continuously during removal of the ossified ligamentum flavum and decompression. EMG bursts occurred, accompanied by decreases in the right-sided SEP and MEP amplitudes. During decompression, after the neuromuscular blockade had fully resolved, right-sided EMG bursts recurred and the right-sided SEP and MEP amplitudes abruptly decreased by more than 50%.
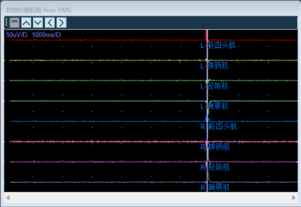
At the end of surgery, the operative field was thoroughly irrigated, with no active bleeding and complete nerve-root release confirmed. MEP and SEP were monitored again during closure, and the right-sided SEP and MEP showed partial recovery compared with the intraoperative nadir.
Intraoperative monitoring during UBE surgery for thoracic ossification of the ligamentum flavum should minimize the effects of anesthetic agents on neurophysiological signals to ensure accurate monitoring. The anesthesiologist should be consulted preoperatively. Neuromuscular-blocking agents should be avoided whenever possible because they may suppress EMG and MEP waveforms. SEP and MEP are also susceptible to suppression by inhalational anesthetics; total intravenous anesthesia is therefore preferred, with stable light-to-moderate anesthesia maintained. Because the interval from induction to the start of surgery is short in this type of procedure, the induction dose of neuromuscular blocker should be limited to what is necessary for intubation, so that an assessable MEP waveform can be obtained as early as possible. In this case, a relatively large dose of neuromuscular blocker was used during anesthetic induction, so a longer time was required for its effect to resolve.
Changes in EMG, SEP, and MEP waveforms across different time points and surgical maneuvers can accurately reflect the effects of surgical manipulation on neurological function. When a maneuver such as traction or electrocautery directly stimulates a nerve root or the spinal cord, abnormal EMG activity, such as bursting potentials, may occur. The surgeon should immediately stop the relevant maneuver and adjust the surgical trajectory to avoid irreversible neural injury. In this case, no decrease was observed in the left-sided SEP waveform. During removal of the ossified ligamentum flavum and decompression, the right-sided SEP amplitude abruptly decreased by more than 50%, then showed a trend toward recovery through closure; the final right-sided SEP remained 35% below the preoperative baseline. The right-sided MEP waveform also decreased abruptly during the same stage but showed a trend toward recovery during closure. When the patient was awakened after surgery, both lower limbs were mobile, suggesting that the sensory and motor conduction pathways were unlikely to have sustained significant injury. Overall, the procedure achieved its objectives of relieving neural compression, preserving lower-limb function to the greatest extent possible, and improving quality of life, with an overall favorable surgical result.
Blood pressure and heart rate should be kept stable to avoid marked blood-pressure fluctuations that could reduce perfusion of the brainstem and neural tissue and affect neurophysiological signals. Intraoperative temperature should be strictly controlled because hypothermia may slow nerve-conduction velocity and interfere with monitoring indices. Electromagnetic interference from electrocautery should be minimized to ensure proper
functioning of the monitoring equipment. Artifact control is also essential for excluding interference unrelated to the surgical maneuver.
In this case, intraoperative MEP during UBE surgery for thoracic ossification of the ligamentum flavum was affected successively by residual neuromuscular blockade and mechanical compression of the spinal cord. The waveforms gradually improved after the procedure was paused and gentle, staged decompression was performed. This case highlights the importance of carefully timing monitoring in relation to the resolution of neuromuscular blockade, maintaining multimodal monitoring throughout the procedure, and performing gentle minimally invasive decompression to reduce the risk of spinal cord injury.
Copyright © NCC Medical Co., Ltd. - Privacy policy
 EN